Table of Contents
This is a direct follow-up to: Part One.
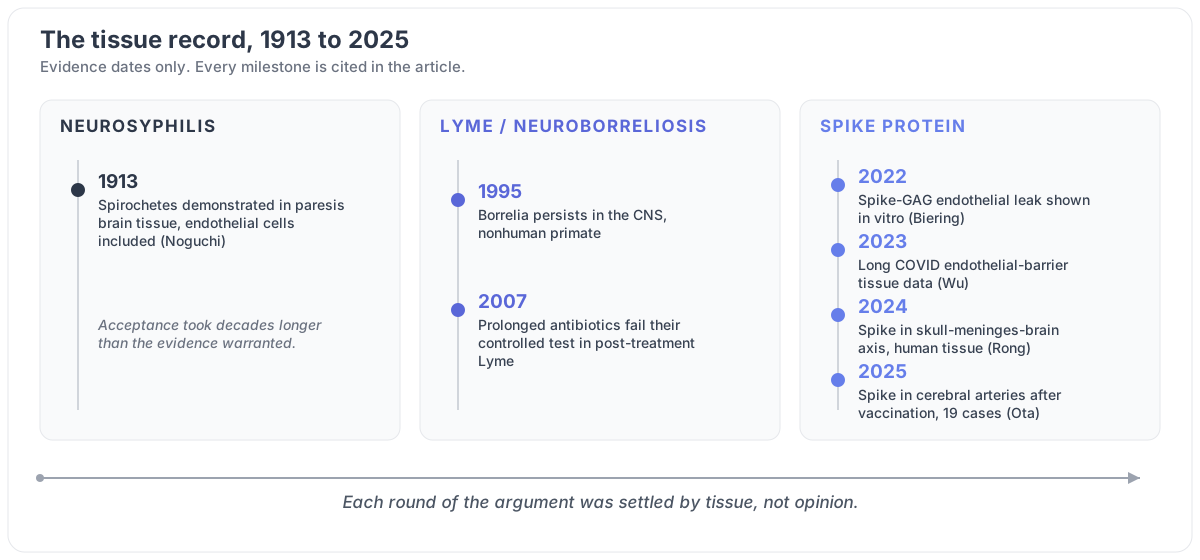
The story covered in Part One did not start in the 1970s with the "discovery" of Lyme. It stretches back over a century, and the century-old evidence is not suppressed fringe material. It is mainstream medicine's own record. Autopsy series from the pre-antibiotic era found spirochetes in the brains of general paresis patients in up to 100 percent of examined cases, localized to gray matter and, critically for this article, inside endothelial and microglial cells (Ghanem 2010, PMID 20626434). Spirochetal invasion of the brain, endothelial cells included, was demonstrated in autopsy tissue in 1913 (Noguchi, PMID 19867640). Acceptance took decades longer than the evidence warranted. The evidence existed. Its lessons were not carried forward.
Now the spike protein is using the same route: the endothelium as the doorway to multi-system illness, while patients with persistent symptoms meet the same dismissal Lyme patients know well. A century-old pattern, repeating in real time.
Framing correction, 4 October 2026. Headers and framing language in this article ("denial playbook", "cover-up", "They've been lying", "corruption is foundational", "fraudulent handling") were descaled to the lag-and-contested-evidence frame the article's own evidence supports. The Burgdorfer quote, the congenital-transmission evidence with its counter-side, the counter-evidence section, and the advocacy sections stand unchanged.
Style pass, 20 October 2026. Callout labels (TRUTH BOMB, SCIENCE SPOTLIGHT, HISTORICAL NOTE, BOTTOM LINE), the paired comparison lists, and the entry-route table were converted to plain prose; "The Hidden Reservoir" was folded into the evasion section; the two closing advocacy sections were merged into one. No claims, citations, or grades changed in this pass. The GAG/RAGE section was added the same day and is covered by the snapshot above.
The Century-Old Endothelial Invasion Blueprint#
Both the Lyme pathogen and the spike protein center their pathology on the same tissue: the endothelium.
We can learn a great deal about spike pathology by studying Lyme disease. The similarities are mechanistic: convergent exploitation of the vascular endothelium. Be precise about what converges. The target is shared; the tools are not. Borrelia burgdorferi is a living, motile, replicating bacterium with adhesins, chemotaxis, and antigenic variation. The spike is a protein with no motility and no replication of its own, and its documented vascular effects are host-mediated responses. Same highway, different vehicles.
Shared Pathogenic Strategies#
Both Borrelia burgdorferi and the SARS-CoV-2 spike protein exploit the endothelium as a gateway to systemic dissemination, by different means.
Endothelial transmigration. For Borrelia this is direct and proven: it crosses endothelial monolayers both between cells (paracellular, at tight junctions) and through them (transcellular), and crossing requires viable, motile spirochetes (Comstock and Thomas 1991, PMID 1890951). The spike does not transmigrate on its own; whole virus infects endothelium via ACE2, and isolated spike inflames and activates the endothelium without any viral replication (Montezano 2023, PMID 37640791).
Fibronectin and integrin engagement. Borrelia's adhesin BBK32 binds fibronectin and glycosaminoglycans and behaves as a catch bond that strengthens under shear, with plasma fibronectin stabilizing vascular attachment (Niddam 2017, PMID 28396443; Hyde 2017, PMID 28270812). The spike's S1 binds beta-1 integrins, the fibronectin receptors, independent of ACE2 (Park 2021, PMID 33918599). Whether the spike exploits a fibronectin bridge under flow has not been tested.
Immune evasion. Borrelia varies its antigens and shelters in biofilms. The spike's documented effects include immune modulation. Both persist in host tissues.
For the route in: Borrelia enters at the tick bite, through skin, and disseminates through blood and lymph after actively crossing the vessel wall. The spike arrives with respiratory infection and viremia, and its endothelial effects run through ACE2-mediated infection by whole virus and through activation by the isolated protein.
The target tissue is the same. Once engaged, both drive pathology along the same vascular highways, one an invading organism, the other a ligand triggering host responses.
Dissemination#
A note on terms: "spike protein" here means the protein itself, whether it arrives with SARS-CoV-2 infection or by other delivery. The mechanism is the point. Where the infection and vaccination evidence bases differ, they are kept separate below.
What happens after entry, for either pathogen:
- The pathogen may be eliminated by host defenses
- It may stay localized, causing initial symptoms (the Lyme skin rash, respiratory illness with spike)
- Within days to weeks it may disseminate through blood and lymphatics
After entering circulation, both show tropism for the same organ systems: skin in Lyme (the rash) against vascular endothelium in spike disease (microclots); the heart in both (Lyme carditis, spike myocarditis); the central nervous system (Lyme neuroborreliosis, spike neuroinflammation); and the joints (Lyme arthritis, spike autoimmune arthritis).
Clinical Parallels#
Lyme disease runs early localized (skin), early disseminated (multiple systems), then chronic disseminated (persistent multi-organ involvement). The spike picture runs acute infection (respiratory), multi-system inflammation (SPED), then long COVID and chronic complications. The parallel is an analogy for orientation: the Lyme column is textbook staging, the "SPED stages" column is not a validated framework.
For Borrelia, the fibronectin mechanism is settled science: plasma fibronectin stabilizes the spirochete's grip on the endothelium under shear through a catch-bond mechanism (Niddam et al., PNAS 2017, PMID 28396443). For the spike, the same idea is an open question. S1 binds beta-1 integrins, the fibronectin receptors, independent of ACE2, but only in static assays so far (Park et al., Viruses 2021, PMID 33918599). Whether the spike exploits a fibronectin bridge under flow has not been tested. A flow-chamber assay with labeled plasma fibronectin and S1 would answer it.
Shared Sugars: Glycocalyx Damage and RAGE#
The fibronectin story above has a second half, closer to the vessel wall. The endothelial surface carries a sugar coat, the glycocalyx, built largely from glycosaminoglycans (GAGs): heparan sulfate, hyaluronic acid, chondroitin sulfate. Borrelia's BBK32 adhesin binds these sugars as part of its grip under shear (Niddam 2017, PMID 28396443). On the spike side, GAG engagement used to rest on binding studies alone. It now rests on removal experiments.
Biering et al. exposed epithelial and endothelial cultures to recombinant spike protein (Nat Commun 2022, PMID 36494335). Spike alone was sufficient for barrier dysfunction in vitro and vascular leak in mice, without viral replication and without ACE2. The mechanistic result, in the authors' words: "removal of HS, HA, or CS, but not sialic acid, inhibited S-mediated endothelial hyperpermeability". Heparin, which mimics heparan sulfate, decreased the spike-induced hyperpermeability. Cells with CRISPR knockouts of heparan sulfate biosynthesis genes (SLC35B2, XYLT2) were less susceptible to spike. Knockouts of heparanase (HPSE), ADAM17, and MMP9 lost their sensitivity to it. Integrins and TGF-β signaling were required, and integrin inhibition reduced the leak in living mice.
The same paper shows how the coat comes off. Spike treatment reduced glycocalyx components on the cell surface and upregulated the enzymes that degrade them: heparanase, hyaluronidases, MMP9, ADAM17. Patient-side work agrees. Plasma from COVID-19 patients induced glycocalyx shedding in cultured endothelial cells and carried more glycocalyx components than healthy plasma, and low molecular weight heparin inhibited the shedding (Potje et al., Life Sciences 2021, PMID 33781826). This is the GAG-shedding mechanism, established at cell-culture grade by two independent groups, one using direct spike exposure and one using patient plasma.
A stripped endothelium would matter less if it reset within hours. The measured time course runs to days. Gultom et al. cultured human aortic and pulmonary microvascular endothelial cells under laminar shear (10 dyn/cm²), exposed them to spike for 24 hours, washed the protein off, and cultured on to 96 hours (Inflammation 2025, PMID 39739157). ICAM-1, the adhesion molecule that anchors leukocytes, rose at 24 hours to a level similar to TNF-α and stayed significantly elevated at 96 hours, 72 hours after the spike was washed away. E-selectin had returned to baseline by then, and leukocyte binding, increased at 24 hours, was no longer detectable at 96 hours. The cells also shifted into a procoagulant state. TNF-α remained the stronger stimulus on the aortic cells at 96 hours, so spike sits in the same order of magnitude as a canonical inflammatory cytokine rather than above it. The dose was 1 μg/ml in culture; the concentration at deposited tissue sites is unmeasured.
The third connection is a receptor. Angioni et al. profiled immune responses at single-cell resolution across COVID-19 disease course and found RAGE pathway activation in monocytes that tracked with severity (Cell Reports Medicine 2023, PMID 37944530). In vitro, THP-1 monocytes bound the spike S1 receptor-binding domain through RAGE, and that interaction enabled monocyte infection. The authors' own summary: RAGE is a functional receptor of SARS-CoV-2, contributing to COVID-19 severity. RAGE already carries weight in this site's persistence model, where RAGE signaling is part of the tolerance trap that keeps spike-loaded cells alive (spike persistence, microclots, and reactivated viruses). The monocyte work hands that receptor a direct spike ligand.
Tight junctions and the glycocalyx are the two structural elements of the blood-brain barrier, so the mechanisms above predict that spike sitting at brain-border vessels should come with barrier and neuroinflammatory injury. That prediction is inference. What the tissue record shows is deposition, in two contexts that stay separate here: after infection, and after vaccination.
Spike at the Brain Borders: Infection Evidence#
Rong et al. used optical clearing, which renders tissue transparent, to search the skull, meninges, and brain for spike (Cell Host and Microbe 2024, PMID 39615487). They found spike protein accumulation in the skull-meninges-brain axis of human COVID-19 patients, persisting long after viral clearance. CSF from long COVID patients carried elevated neurodegeneration markers, and proteomics of human skull, meninges, and brain tissue showed dysregulated inflammatory pathways and neurodegeneration-associated changes. In mice, injection of spike protein alone induced neuroinflammation, proteome changes in the same axis, and anxiety-like behavior, and it worsened outcomes in models of stroke and traumatic brain injury. Vaccination reduced, and did not eliminate, spike accumulation after infection in the mice. The authors state their conclusion at contribution strength: persistent spike at the brain borders "may contribute" to lasting neurological sequelae.
Spike at the Brain Borders: Vaccination Evidence#
Ota et al. examined cerebral-artery tissue from 19 hemorrhagic stroke cases from 2023 to 2024, with vaccination and infection histories recorded (J Clin Neurosci 2025, PMID 40184822). Immunohistochemistry detected spike protein in 43.8 percent of vaccinated patients, predominantly in the intima of cerebral arteries, in some cases up to 17 months after vaccination. CD4-, CD8-, and CD68-positive cells infiltrated the spike-positive vessels, without active inflammatory changes. In situ hybridization on selected cases detected spike-encoding mRNA of both vaccine and virus origin, and nucleocapsid protein was negative in every case, which argues against active infection. Spike positivity appeared only in female patients (P = 0.015 as reported).
The limits sit in the record itself. The authors state that asymptomatic SARS-CoV-2 infection cannot be excluded as the source and call for global replication studies. A published critical appraisal (Mueed et al., J Clin Neurosci 2025, PMID 40267596) lists the absence of a control group, reliance on negative nucleocapsid staining to exclude prior infection, a small and unbalanced sample, and unconfirmed RNA detection techniques, and concludes that these problems undermine causal inferences regarding vaccine-related spike protein persistence. Nineteen uncontrolled cases show detection in tissue. They do not show that spike caused the strokes.
What Would Move These Grades#
Independent replication of the GAG-removal result in other endothelial beds and other laboratories would move it from single-study to replicated. The cerebral-artery finding needs what the appraisal lists: matched unvaccinated controls, serial serology, validated tissue methods. The in vitro dose of 1 μg/ml has no measured counterpart at tissue deposits, so concentration-matched experiments would test whether the GAG mechanism operates at deposited levels. Neither brain-border study measured barrier function in the same subjects, so deposition and leak are linked by hypothesis only. The GAG-glycocalyx work stands at cell-culture grade. Human brain-border persistence has two tissue findings, one after infection and one after vaccination, the second small and contested. What the deposited spike does inside those vessels is the open measurement, and both papers state their own limits.
Cardiac Manifestations#
Lyme carditis occurs in roughly 8 percent of patients, median 21 days post-infection, with AV block, myopericarditis, and conduction disturbances, from direct spirochetal invasion of cardiac tissue. It is often dismissed as "rare" with a "good prognosis" (Yeung and Baranchuk, J Am Coll Cardiol 2019, PMID 30765038).
The spike cardiac picture runs chest pain, ECG abnormalities, arrhythmias, postural orthostatic tachycardia syndrome, chronic perimyocarditis with ventricular failure, arterial wall inflammation, and microthrombosis, from endothelial injury and inflammation (Montezano AC, et al. SARS-CoV-2 spike protein induces endothelial inflammation via ACE2 independently of viral replication. Sci Rep 2023, PMID 37640791). It is often dismissed as "anxiety" or "post-viral syndrome".
Persistent cardiac and neurological symptoms in syphilis and Lyme were labelled "hysteria" or "hypochondria" before the tissue evidence settled the question. The analogous labels now attached to long COVID ("anxiety", "post-viral stress") follow a documented historical pattern. The pattern is a fact of history; the label is not evidence in either direction.
Persistent Infection and Immune Evasion#
Borrelia has a documented evasion arsenal: pleomorphism into cystic and granular forms (documented in autopsy studies), biofilm formation that protects against immune clearance and antibiotics, CNS persistence documented at autopsy, and polymicrobial synergy that defeats single-target therapy (Čorak N, et al. Int J Mol Sci 2023, PMID 36982667). It also turns up in unexpected tissues. That is the practical lesson for this article: a pathogen that hides in biofilms, switches form, and occupies unexpected tissues does not simply "clear", and the spike's documented persistence in tissue reservoirs has to be read with that mindset.
The spike's evasion picture, as currently documented: tissue persistence months post-infection and post-vaccination (the brain-border evidence above), alterations to host cell function (mitochondrial and epigenetic), autoimmunity through molecular mimicry, and apparent resistance to simple mono-therapies.
Both conditions generated documented professional conflict: psychiatric dismissal of persistent symptoms, and licence actions against clinicians treating outside guideline consensus. The disputes are real. On the tissue evidence, they get settled by data, not argument.
A Century of Lag: From Syphilis to SPED#
A century of published findings, not carried forward#
Forensic pathology work is the record here: spirochetes have been observed in the brains of neurodegenerative patients for over a hundred years. The evidence was published in the standard literature of its day. What it met was not erasure but inertia, and the reflexive "contamination" objection for anyone who pushed.
The findings sat in the record while clinical acceptance took decades longer than it should have. That is the documented mechanism: inertia and contested interpretation, not suppression.
Willy Burgdorfer, Ph.D., the namesake of the bacterium, was sharply critical of the serology research economy of his era:
"Serology or serology plus has to be started from scratch with people that don't know beforehand the results of their research, just because they have to get the money."
His complaint was about funding incentives shaping research questions. That is a documented critique of how research agendas form; it is not, by itself, proof that results were suppressed.
Transmission beyond the tick bite: an open question#
Investigations into the microbiology of Borrelia challenged the simple "tick bite" narrative. Congenital transmission is suggested by molecular and microscopic diagnostics in a 2026 case report (Bemis, Microorganisms 2026, PMID 41753693), and documented for relapsing-fever Borrelia as far back as 1969 (Fuchs, JAMA 1969, PMID 5818572). The counter-side deserves its say: a 2024 mouse study found no congenital Lyme transmission (Velásquez et al., Microbes Infect 2024, PMID 38380602). The question is open, not closed. Beyond that, multiple arthropod vectors outside Ixodes ticks, and the presence of Borrelia in human fluids, have both been reported; neither is settled.
Professional conflict and licence actions#
Lyme clinicians who treated persistent symptoms outside guideline consensus faced licence investigations, and some lost them. The COVID era saw analogous professional and institutional actions against dissenting clinicians. Both episodes are documented; the intent behind each remains contested.
The documented sequence:
- Complexity dismissed: persistent symptoms attributed to psyche ("it's all in your head")
- Messengers sanctioned: licence threats and professional discipline against treating clinicians
- Patients relabelled: "medically unexplained symptoms" as a diagnostic resting place
- Guidelines outlast the evidence: conservative positions revised only after tissue data accumulate
The Lyme transmission disputes primed a generation of patients and clinicians to recognise how slowly official positions can move; the SARS-CoV-2 aerosol episode repeated the pattern on a months-long timeline instead of a decades-long one.
The co-infection reality#
Decades of clinical and patient-advocacy work consistently emphasized that Lyme disease is rarely a monoinfection: B. miyamotoi joins the picture, and co-infections like Bartonella and Babesia create more severe, complex illness. The lesson generalizes. Treating one pathogen in a polymicrobial illness is a recipe for failure, and long COVID shows the same shape, with reactivation of latent viruses (EBV, HSV) and bacterial imbalances common.
The Convergence: A Century in the Making#
The intersections between these two contested conditions are not coincidental. Both ran into the same problem: an acute-event model of infection confronting pathogens and proteins that persist.
Lessons Unlearned: Historical Continuity#
Long COVID tissue data is doing what chronic-Lyme researchers spent decades arguing needed doing: documenting persistence directly rather than inferring it from symptoms. Whether it confirms their broader claims remains open.
The parallels that hold, stated plainly:
- Persistence denied until tissue forced the issue. In Lyme, nonhuman-primate and autopsy data; in long COVID, accumulating tissue data (Wu 2023, PMID 37103631).
- Patients psychiatrically labelled while the biology was worked out. Documented for syphilis and Lyme (Aronowitz 1991, PMID 2034186); the long COVID analogue is current.
- Treatment fought out in public. Licence actions in the Lyme era; protocol disputes in the COVID era.
The parallel that does not hold: the Lyme treatment story is not a clean suppression story either, because prolonged antibiotics failed their controlled test in post-treatment Lyme (Feder 2007, PMID 17914043). The lesson cuts both ways: contested medicine still has to win on data.
The acute-only model of infection has now failed two patient populations across a century. Persistence, complexity, and immune evasion are the lessons, and tissue evidence, not argument, is what settles them.
Where the Analogy Breaks#
Counter-Evidence & Limitations
- A living pathogen versus a glycoprotein. B. burgdorferi is self-propelled, replicating, and chemotactic; its dissemination is an active bacterial process (Hyde 2017, PMID 28270812). The Spike has neither motility nor replication. Its vascular effects, real as they are, are host-mediated inflammatory and signaling responses (Avolio 2023, PMID 37268620).
- Whole virus versus isolated protein. In patients, acute-COVID endothelial injury is driven by whole-virus ACE2-mediated infection plus systemic inflammation (Montiel 2022, PMID 35219085). Isolated-spike experiments, including the intravenous-spike mouse work cited above, are mechanistic evidence, not a direct model of patient disease.
- The Lyme controversy cuts both ways. Randomized trials found prolonged antibiotics did not benefit patients with persistent symptoms after treated Lyme disease (Feder 2007, PMID 17914043), and the sociology of contested illness runs in every direction (Aronowitz 1991, PMID 2034186). Persistent-symptom claims in spike pathology have to meet the same evidentiary bar the chronic-Lyme claims failed. The way to meet it is tissue data, and for long COVID that data is now accumulating (Wu 2023, PMID 37103631).
The Way Forward#
The path has already been carved out by the researchers and patients who came before. Healing requires operating outside the failed medical machine.
The pathway, learned from decades of Lyme advocacy:
- Find independent clinicians who understand complex chronic illness
- Educate yourself beyond mainstream medical narratives
- Trust clinical evidence over restrictive, politicized guidelines
- Build patient communities for knowledge sharing and support
- Pursue multi-system, personalized approaches that address persistence and inflammation
International Lyme and Associated Diseases Society FLCCC Post-Vaccine Treatment Protocol
The work is being advanced by independent physicians applying the principles of complex chronic illness management, patient advocates carrying the lessons of the Lyme wars, researchers who prioritize data over funding incentives, and clinical innovators building the multi-pronged protocols these conditions demand.
What you can do with that, informed by a century of this struggle:
- Recognize the historical pattern. The dismissal has a century of precedent, and the tissue record eventually settled it before
- Find your allies: doctors and communities operating on the principles these researchers fought for
- Educate yourself on the science of persistence, endothelial dysfunction, and immune evasion
- Do not accept dismissal. Patient perseverance is the most documented force for change in this record
The medical establishment has failed on both fronts. We do not need their permission to heal, and we can stand on the work of the researchers who came before us.
Key Research & Legacy#
Key Literature:
- MS and Lyme research summary (PDF)
- Noguchi: A demonstration of Treponema pallidum in the brain in cases of general paralysis, J Exp Med 1913 (PMID 19867640) - the 1913 tissue proof
- Ghanem: Neurosyphilis, a historical perspective and review, CNS Neurosci Ther 2010 (PMID 20626434) - the paresis autopsy record
- Miklossy: Alzheimer's disease - a neurospirochetosis. Analysis of the evidence following Koch's and Hill's criteria, J Neuroinflammation 2011 (PMID 21816039) - hypothesis-grade
- MacDonald: Plaques of Alzheimer's disease originate from cysts of Borrelia burgdorferi, Med Hypotheses 2006 (PMID 16675154) - hypothesis-grade; Med Hypotheses is a hypothesis-tier venue, treat accordingly
Modern Corroboration:
- Plasma fibronectin stabilizes Borrelia-endothelial interactions under vascular shear, PNAS 2017 (PMID 28396443) - Borrelia-specific
- Spike protein induces endothelial inflammation via ACE2, independent of viral replication, Sci Rep 2023 (PMID 37640791)
- Spike protein-induced microvascular damage, mouse and human pericytes, Signal Transduct Target Ther 2023 (PMID 37268620)
- Oxidative stress-induced endothelial dysfunction in COVID-19, eBioMedicine 2022 (PMID 35219085)
- Damage to endothelial barriers and its contribution to long COVID, Angiogenesis 2024 (PMID 37103631)
- Spike glycoprotein binds beta-1 integrins, Viruses 2021 (PMID 33918599)
- Borrelia dissemination and invasion review, Front Immunol 2017 (PMID 28270812)
- Borrelia invasion of cultured endothelial cells, Microb Pathog 1991 (PMID 1890951)
- Borrelia, host-derived proteases, and the blood-brain barrier, Infect Immun 2005 (PMID 15664945)
- Borrelia persists in the central nervous system in the nonhuman primate, Ann Neurol 1995 (PMID 7574465)
- Pleomorphic variants of Borrelia burgdorferi, Int J Mol Sci 2023 (PMID 36982667)
GAG, Glycocalyx, RAGE, and Brain Borders (added 20 October 2026):
- Spike triggers barrier dysfunction and vascular leak via integrins and TGF-β signaling, Nat Commun 2022 (PMID 36494335) - removal of heparan sulfate, hyaluronic acid, or chondroitin sulfate blocks spike-mediated hyperpermeability
- Heparin prevents in vitro glycocalyx shedding induced by plasma from COVID-19 patients, Life Sciences 2021 (PMID 33781826)
- Sustained vascular inflammatory effects of SARS-CoV-2 spike protein on human endothelial cells, Inflammation 2025 (PMID 39739157) - ICAM-1 still elevated 96 h after a 24 h spike exposure under flow
- RAGE engagement by SARS-CoV-2 enables monocyte infection and underlies COVID-19 severity, Cell Rep Med 2023 (PMID 37944530)
- Persistence of spike protein at the skull-meninges-brain axis may contribute to the neurological sequelae of COVID-19, Cell Host Microbe 2024 (PMID 39615487)
- Expression of SARS-CoV-2 spike protein in cerebral arteries: implications for hemorrhagic stroke post-mRNA vaccination, J Clin Neurosci 2025 (PMID 40184822) - 19-case uncontrolled series
- Critical appraisal of the cerebral-artery spike study, J Clin Neurosci 2025 (PMID 40267596)
For over a century, patients with persistent spirochetal illness were told they were wrong, and the tissue evidence eventually sided with the biology. Spike protein injury patients are hearing the same dismissal now. The researchers who did that work deserve the credit, and the patients deserve the workup. The path to healing is difficult, but it is real, and it is paved with the evidence they fought to surface.
This analysis builds on the important work of Walter M. Chesnut and his research into Spike Protein Endothelial Disease. Follow his work at WMCResearch.substack.com.
Educational content, not medical advice. Work with a clinician for diagnosis/treatment.