Table of Contents
Key Takeaways
- Classic ADME pharmacokinetics does not describe these products. One injection is at least three exposures with different fates: the intact particle, the mRNA, and the expressed protein, plus the free lipids after the particle dismantles. [MECHANISTIC]
- The particle you are exposed to is not the particle that was manufactured. Within minutes the PEG-lipid shell is shed and replaced by a biocorona dominated by apolipoproteins including ApoE, which changes where the particle goes. [MECHANISTIC]
- Distribution is decided by capillary anatomy. Sinusoidal organs (liver, spleen, bone marrow) and fenestrated-capillary organs (adrenals, kidneys, small intestine, thyroid, choroid plexus, eye) receive the bulk; continuous-capillary organs depend on transcytosis. 'The LNPs go everywhere' is as wrong as 'it stays in the arm'. [HYPOTHESIS]
- The regulatory biodistribution package was thin: the pivotal Pfizer rat study tracked a radiolabelled lipid component for 48 hours with a luciferase-substitution assumption, and levels in liver, spleen, adrenals and ovaries were still rising at the last timepoint. No human biodistribution study exists. [MECHANISTIC]
- A substantial fraction of particles in every batch is empty, and empty LNPs are highly inflammatory on their own (Ndeupen 2021). The 2026 Seger, Gutschi and Seneff review argues the particle is an active biointerface whose membrane interactions perturb the PI cycle with downstream NF-kB, MAPK, JAK/STAT and mTOR signalling. [MECHANISTIC, hypothesis-graded]
- Detection is not translation. Vaccine-derived RNA sequences are reliably found in blood for up to 28 days and in tissues longer, but no study demonstrates intact, translation-competent mRNA at late timepoints, and the free-spike findings in myocarditis are acute-phase. The vesicle-relay explanation is handled in the exosome-relay article. [ESTABLISHED for detection, HYPOTHESIS for persistence mechanisms]
Why this article exists
This site carries two clusters that meet at the vial. The forensics cluster documents what got into the products: residual plasmid DNA, the SV40 enhancer sequence, process-1 versus process-2 divergence. The persistence cluster documents what spike does once it is made: microclots, tissue reservoirs, tolerance failure. A third layer sits between them and has never had its own page here: the lipid nanoparticle, the thing that actually gets injected.
That gap matters for a reason specific to this site's model. Persistent antigenic drive plus clearance failure plus corrupted tolerance is the loop this site proposes for chronic spikeopathy. Every node in that loop is usually argued about as if the particle were a neutral courier. The pharmacological literature does not support that reading, and in 2026 the person who assembled the case most carefully was a retired pharmacist, Maria Gutschi, together with Falko Seger and Stephanie Seneff, in a peer-reviewed review in Acta Pharmaceutica Sinica B (PMID 42764981). This article walks the particle's path from vial to organ, states what is measured, what is inferred, and what is proposed, and calibrates the loudest claims in circulation against what the primary documents actually say.
Credit where it belongs
The frame this article follows is not mine. The multi-part biodistribution analysis (Part 1, Part 2, Part 3) and the fenestrated-endothelium synthesis (LNP biodistribution is mostly dependent on fenestrated epithelium) are Gutschi's, and the active-biointerface thesis is the Seger, Gutschi and Seneff review's. The biocorona literature belongs to the Cullis group and colleagues (Francia et al. 2020, PMID 32786370); the tissue-selectivity mechanism to Kimura and Harashima (PMID 37004796); the empty-LNP inflammatory finding to Ndeupen and colleagues (PMID 34841223); the complement and anti-PEG work to the Szeged group around Szebeni, Mészáros and Dézsi (PMID 35146583, PMID 38933697). Where the site's existing articles intersect (residual DNA, insertional mutagenesis, the exosome relay), those articles keep their own credit lines intact; McKernan's prior deposit work governs the DNA side and is credited there.
One injection, three exposures
Pharmacokinetics has a standard frame: absorption, distribution, metabolism, excretion. Gutschi's opening argument, and it holds, is that the frame cannot describe these products because a single injection contains at least three pharmacological objects with different fates:
- the intact particle, an assembly of four lipids around the mRNA,
- the mRNA itself, released or retained,
- the expressed protein, made wherever transfection succeeded,
plus a fourth that only appears after the particle starts dismantling: the free lipids, which have their own tissue residence and their own chemistry.
You cannot put one compartment model around that. Gutschi proposes replacing ADME with absorption, biodistribution, transfection, gene translation, and exosome formation and elimination, and cites a pharmacokinetic specialist's attempt to model the platform that needed eleven compartments before giving up. The practical consequence for a patient or clinician is simpler: no single number, no half-life you were told, describes "the vaccine". Every claim about persistence or clearance has to say which of the three objects it is about. Most public claims do not.
The biocorona: the particle you get is not the particle they made
The first thing that happens after injection is not transfection. It is adsorption. The particle meets interstitial fluid and lymph, then plasma, and its surface changes within minutes: the PEG-lipid shell, the part that keeps the particles from clumping in the vial, is shed and exchanged, and the particle picks up a coat of host biomolecules, apolipoproteins prominent among them, including ApoE. That coat is the biomolecular corona, reviewed for gene-therapy LNPs by Francia, Schiffelers and Cullis (PMID 32786370). Its consequence is stated plainly in that literature: the corona, not the manufactured surface, defines the particle's biological identity and its traffic. An ApoE-decorated particle is handled like a lipid particle of the kind the liver and adrenal cortex process every day. That is not a speculation; it is the accepted mechanism of tissue-selective LNP delivery, the same machinery Onpattro (patisiran) rides into hepatocytes, and Kimura and Harashima set it out as such (PMID 37004796).
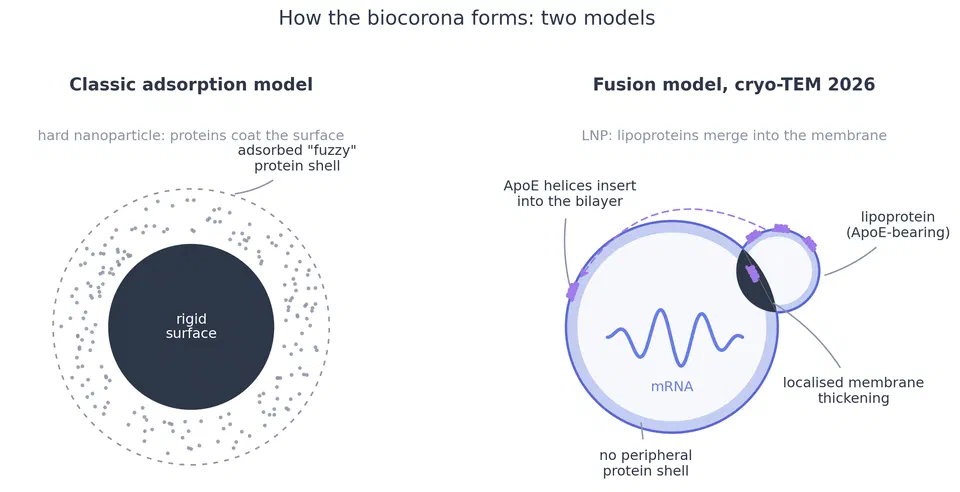
Update, 2026-09-27: direct imaging now challenges the shell picture itself. Grumelot, Mohammed and colleagues, with Whitehead and Mahmoudi as corresponding authors, visualised LNP-protein interactions by cryo-transmission electron microscopy and report that, unlike the discrete "fuzzy" shells of hard nanoparticles, "LNPs displayed no peripheral protein shell"; instead "LNP membranes undergo localized thickening and electron-dense remodeling consistent with lipoprotein integration rather than surface adsorption" (Nano Letters 2026, PMID 42677364). Proteomics in the same study identified apolipoproteins as the dominant associated proteins: "Apolipoproteins accounted for a mean of ∼25–55% of total LFQ intensity across the LNP fractions (varying by LNP formulation), compared with approximately 18% in neat plasma processed in parallel", indicating selective association, and similar features appeared in extracellular vesicles, suggesting the behaviour is shared among lipid-based carriers. The fusion model keeps everything this section relies on, PEG-shell shedding, the apolipoprotein coat, ApoE, the Francia corona work and the Kimura and Harashima selectivity mechanism, and sharpens it: the corona proteins are not passengers stuck to a surface, they merge into the membrane, which is a cleaner explanation of why corona composition changes particle behaviour so profoundly. Two cautions travel with the finding. It is one in vitro study, published 2026, and it supersedes an illustration, not the corona concept. And the composition side is open: the 25-55 percent range is explicitly "varying by LNP formulation", and Mo and colleagues showed directly that ApoE-LNP behaviour "is highly dependent on the LNP composition", though with porphyrin-lipid LNPs rather than the vaccine lipids (JACS 2026, PMID 41711348). The exact corona composition of the authorised products' lipids is therefore an extrapolation target, not a measured number.
Two corollaries follow, and both are under-appreciated.
First, batch variability in the particle becomes biological variability in the patient, because a differently sized or differently charged particle draws a different corona. Second, patient variability becomes particle variability: the corona a hyperlipidaemic, pregnant, or elderly patient forms from the same vial is not the corona a lean twenty-year-old forms. Neither source of variance was characterised at population scale before rollout.
Anatomy decides: four compartments
The most useful idea in Gutschi's series is also the simplest: LNPs do not distribute by diffusion, the way small-molecule drugs do. They are roughly chylomicron-sized particles, and they go where the vasculature lets particles go. Her synthesis, which this site grades [HYPOTHESIS] as a mapping while the underlying capillary anatomy is textbook, sorts the body into four exposure compartments:
Sinusoidal organs (liver, spleen, bone marrow) have open-capillary beds built to exchange large particles: they take the bulk load. Fenestrated-capillary organs (adrenals, kidneys, small intestine, thyroid, the choroid plexus, the eye behind the retina) come next, and this mapping explains organ patterns that look mysterious otherwise: the adrenal and ovarian signal in the Pfizer rat data, the thyroid and eye symptom clusters in pharmacovigilance. Continuous-capillary organs (heart, skeletal muscle, brain under the blood-brain barrier) take up particles only by transcytosis, a slower, receptor-mediated route; Gutschi's proposal for the heart is that it is not especially permissive but simply first in line after the thoracic duct empties into the great veins, so it sees a high first-pass concentration of whatever transcytosis can carry. Low-flow and barrier tissues see least, with the specific caveat that the corpus luteum, after ovulation, is a fenestrated exception inside an otherwise tight organ, one of several reasons the pregnancy and ovarian findings deserve better studies than they got.
Read this mapping as an organising hypothesis, not a measurement. What supports it: the regulatory rat distributions (next section), the Onpattro liver-tropism baseline, and the fenestration literature. What would refine it: human data, which do not exist.
What the regulatory studies actually measured
The pivotal Pfizer biodistribution study, the one released through the Japanese regulator and known informally as the Japanese study, is a regulatory document and primary for what it is: intramuscular dosing in rats, tissue radioactivity measured by liquid scintillation counting of a radiolabelled, non-metabolisable lipid marker, and a 48-hour observation window. Three rats per sex per timepoint, as Gutschi reads the study report (Part 1). Two limits matter more than any single number in it. The label sits on a lipid, so the method cannot distinguish intact particles from lipid debris, cannot see the mRNA at all, and cannot see expressed protein. And the 48-hour cutoff arrives while signal in liver, spleen, adrenals and ovaries is still rising, so the study's honest conclusion is that distribution was underway and uncharacterised at its endpoint, not that clearance was demonstrated. (Full study report: held copy; FDA document release via phmpt.org.)

The substitution assumption deserves its own sentence: regulators accepted luciferase-mRNA particles as surrogates for spike-mRNA particles on the argument that the coding sequence should not change the particle. How a given mRNA packs changes particle size and shape and corona behaviour, and that assumption was never verified for the authorised products.
Moderna, per Gutschi's reading of the record, escaped a product-specific biodistribution requirement by pointing to one mouse study of a different product, its failed CMV candidate mRNA-1647, presented at Science Day 2022. The published record that fills the gap best is the pharmacokinetics work the field has finally started doing on its own next-generation lipids. The Lipid 5 study (Ci et al., PMID 37208184) measured the ionizable lipid by two orthogonal methods after IV dosing in rats: peak concentrations in most tissues within 1 hour, concentration in urinary and digestive tracts by 10 hours, almost exclusively liver and intestines by 24 hours, and complete radiolabel clearance within 168 hours, consistent with hepatobiliary and renal excretion. That is the good news, and it should be stated: a biodegradable ionizable lipid can be cleared.
The same study tracked mRNA and translated protein separately, and this is where it becomes essential reading. In Gutschi's close reading of the tissue figures, cardiac mRNA signal was short-lived while translated protein persisted to the 7-day endpoint, and ocular tissue showed mRNA signal out of proportion to its lipid signal, implying the three objects do not travel together. Biodistribution of lipid is not biodistribution of mRNA is not biodistribution of protein. Those two observations are hers, read off primary figures, and deserve independent verification, but the paper's own design, tracking all three, concedes the principle. Follow-on work has continued in 2026: whole-body PK of lipid, mRNA and protein in mice (PMID 41927964), of lipid, mRNA and expressed antibody (PMID 42373925), and a physiologically based pharmacokinetic model for LNP-mRNA products (PMID 42527729). In swine, protein expression in all major organs after IV mRNA-LNP infusion is published (PMID 39253356). The field is measuring now what was not measured in 2020, and the direction of the findings is not reassuring.
No human biodistribution study exists. The method does not exist to do one ethically at scale. Every sentence about where these products went in humans is inference from rats, mice, swine, organ-on-chip work, and circumstantial human signals.
The empty fraction is not inert
Every batch contains particles with no mRNA inside. The encapsulation efficiency figure quoted in manufacturing (98 percent and up) measures how much of the mRNA ended up in some particle, not how many particles contain mRNA. The Seger, Gutschi and Seneff review assembles the evidence that the empty fraction is substantial: 12 to 80 percent depending on formulation and method, likely 15 to 35 percent for the authorised products (PMID 42764981).
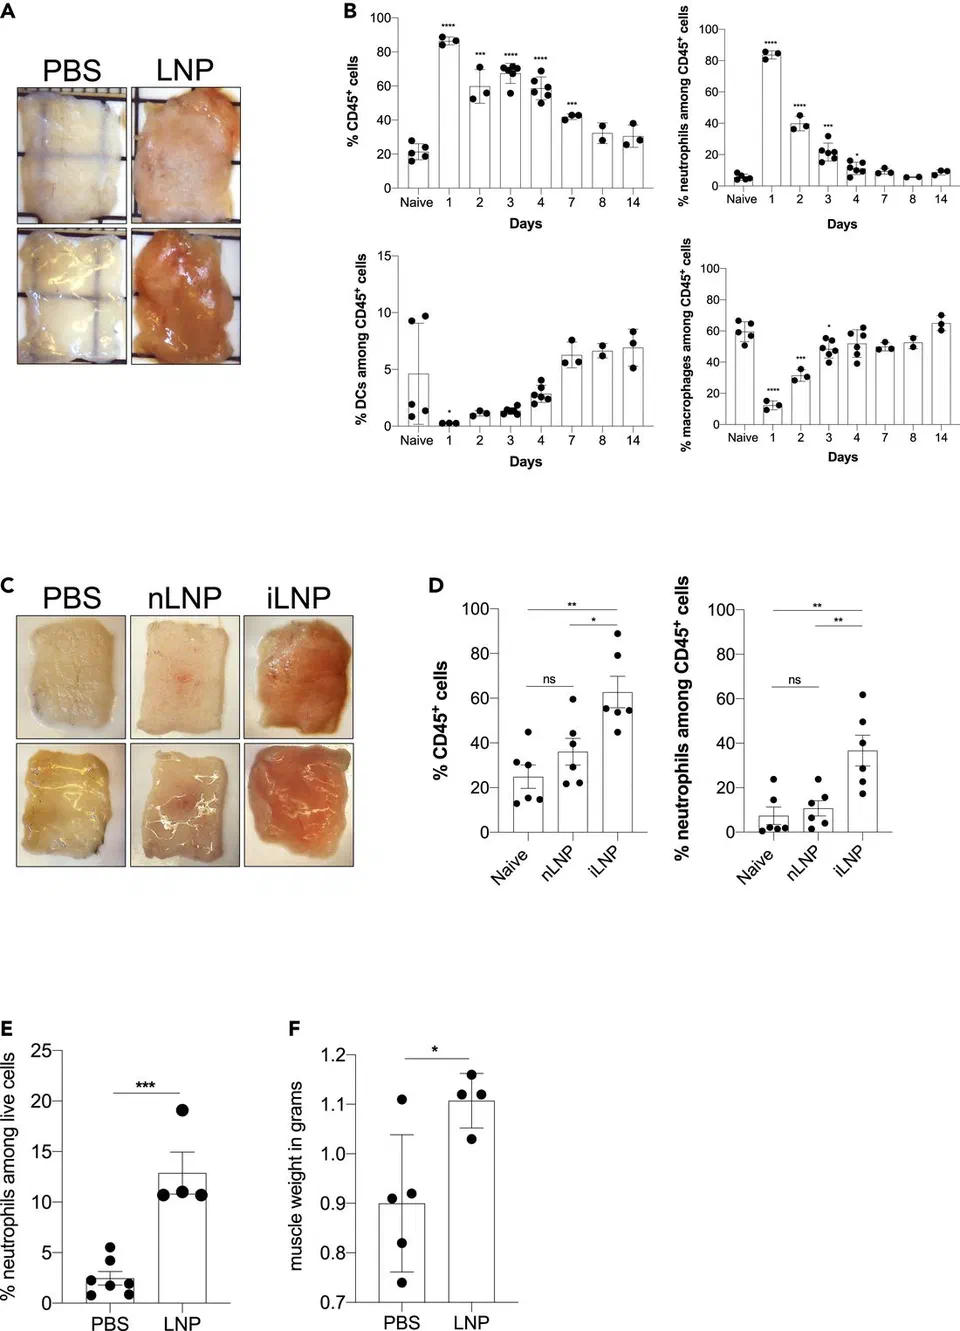
Empty does not mean silent. Ndeupen and colleagues showed the platform's LNP component, without relevant payload, is, in their title's own words, highly inflammatory: intradermal and intramuscular injection in mice produced rapid, robust inflammatory responses with massive neutrophil infiltration, diverse inflammatory pathway activation, and inflammatory cytokine and chemokine production; the same dose intranasally produced lung inflammation and high mortality (PMID 34841223). This is 2021 work, published months before the campaigns, and it was not a reason anyone paused.
The myocarditis literature now triangulates the same point from the clinical end. In adolescents and young adults hospitalised with post-vaccination myocarditis, Yonker and colleagues found immune profiles essentially indistinguishable from matched vaccinated controls, but markedly elevated free, unbound, full-length spike (33.9±22.4 pg/mL) in the affected group and none in the controls (PMID 36597886). Tsang and colleagues implicated natural killer cells in the acute injury (PMID 38521068). And Mori and colleagues, in 2026, supplied the host-factor half of the picture: a human case-control series showing mitochondrial abnormalities in affected patients, plus a mouse model (Polg+/D257A, proofreading-deficient mitochondrial DNA polymerase) in which vaccination reduced left ventricular ejection fraction and induced cardiac immune infiltration, with mitochondrial ROS driving RIPK3-dependent necroptosis in cardiomyocytes, and protection by oestrogen-signalling augmentation with bazedoxifene (PMID 41922346). Susceptibility is not uniform. It tracks mitochondrial robustness, which is precisely the kind of variable no screening covered.
L-DMD: the membrane hypothesis, stated at its true strength
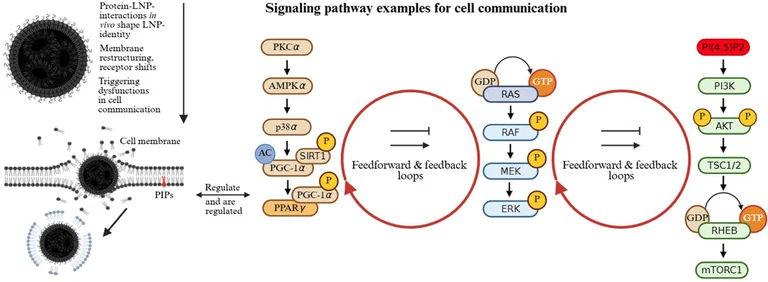
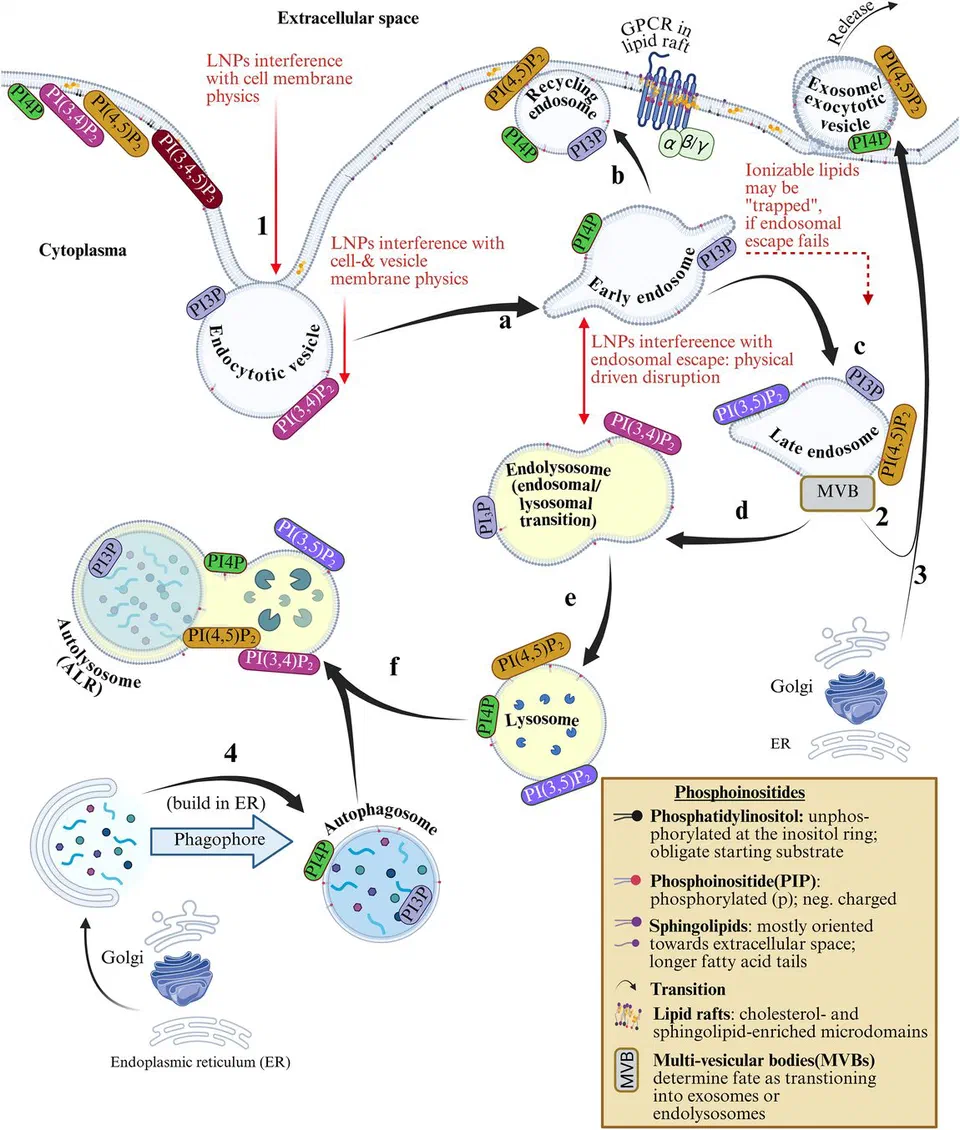
The Seger, Gutschi and Seneff review's central proposal is this. Ionizable lipids are built to become positively charged in acid; that is how they tear out of the endosome. But cell membranes are negatively charged, and the same lipids can insert into membranes generally, perturbing lipid architecture. The review hypothesises the phosphatidylinositol cycle, the membrane-addressing system that tags compartments and routes vesicle traffic, as the primary site of disturbance, with downstream consequences through NF-kB, MAPK, JAK/STAT and mTOR signalling, and measured effects on PPARgamma (a metabolic and anti-inflammatory brake) and cytochrome P450 enzymes. They name the systemic effect lipid-nanoparticle-driven membrane dysfunction, L-DMD (PMID 42764981).
The CYP finding is the most immediately clinical. Suppression of CYP3A4, 2C9, 2C19 and 1A2 expression, apparently transient and cytokine-mediated on the order of weeks, implies that narrow-therapeutic-index drugs metabolised by these enzymes (clozapine, warfarin, several antiepileptics and immunosuppressants) can run high in the weeks after dosing. The review documents the first such case, a profound neutropenia from a clozapine-vaccine interaction. Case reports are an accepted evidence class for drug interactions. Nobody was told to take a medication history before a pop-up clinic.
What the review explicitly does not claim deserves equal billing, in its authors' own words: it is hypothesis-generating; most supporting data are mouse and in vitro under dosing conditions that may not translate to intramuscular human exposure; no causal relationship with any disease state is established; longitudinal human validation is lacking. This site grades the L-DMD cascade [HYPOTHESIS], [LOW-MODERATE] confidence, and treats it as the best available organising frame for findings (CYP, PPARgamma, mitochondrial, persistence-adjacent) that otherwise float unconnected. The refutation tests are straightforward and are the review's own proposed experiments.
The immune system sees the particle: PEG and complement
The PEG-lipid is not immunologically invisible, and 2026 quantified what the campaigns did to population anti-PEG immunity. Facskó and colleagues analysed 325 donor plasma samples: recipients of PEGylated mRNA-LNP vaccines (Comirnaty or Spikevax) showed increased anti-PEG antibody levels and qualitative changes in binding behaviour, with progressively higher avidity toward larger and more complex PEG-bearing structures, strongest binding to PEGylated liposomes, and the most pronounced changes after Spikevax; polysorbate-containing or PEG-free vaccines did not produce comparable effects (PMID 42514893). A 2026 review covers mechanisms and consequences (PMID 42362057).
Causality for the anaphylaxis phenotype now has an animal model. Barta and colleagues immunised pigs against PEG (anti-PEG titres rising 5-10-thousand-fold), then gave one-third of a human Comirnaty dose intravenously: all six animals developed anaphylactic shock within one minute, with maximal pulmonary hypertension, granulo- and thrombocytopenia, skin reactions, and parallel C3a and thromboxane B2 rises, consistent with complement activation (PMID 38933697). The same group's earlier work had flagged complement activation as a contributing mechanism in a hypersensitive porcine model (PMID 35146583), and their 2026 follow-up documents transfection and inflammatory cytokine upregulation in pigs given Comirnaty (PMID 42503016). The caveat is the model's design: hyperimmune animals, intravenous route. What it establishes is mechanism and a plausible order of events for the rare human reactions, not their frequency.
The metastasis signal, calibrated
In June 2026 the sharpest preclinical result of the whole LNP literature arrived: Wang and colleagues, in Nano Today, reported that an mRNA-vaccine-type LNP promoted experimental tumour metastasis in mice via mtDNA-induced neutrophil activation and NETosis (Nano Today 2026). The mechanistic chain: intramuscular LNP injection injured muscle, damaged cells released mitochondrial DNA, circulating mtDNA engaged TLR9-MyD88 and cGAS-STING signalling, neutrophils accumulated in lung with an N2-like pro-metastatic phenotype, NETosis deposited histones, and histone bridging increased tumour-cell adhesion to endothelium, increasing metastatic capture. Knockout mice (Tlr9-/-, Myd88-/-, Sting-/-) and interventions (neutrophil depletion, Cl-amidine, DNase I) localised the effect. Empty particles and GFP-mRNA particles both did it; an antigen-matched E6/E7 vaccine arm protected against tumour while the same particle promoted metastasis, the double-edged sword in one experiment.
Two calibrations keep this where the evidence is. First, formulation dependence: the ALC-0315-containing (Pfizer-like) formulations produced the effect and the SM-102 (Moderna-like) formulation did not, which means the hazard belongs to a specific supramolecular assembly, not to the letters LNP, and one mouse model is not a product ranking. Second, scope: these are challenge models, tumour cells injected deliberately, metastatic burden as the endpoint; nothing in the study shows cancer initiation, and there are no human data. What the study does remove is the excuse that the delivery vehicle is biologically inert. The receptor-level target it lands on, cGAS-STING, is the same node this site already treats in the baicalin monograph.
Detection is not translation
A consistent finding across cohorts: vaccine-derived RNA sequences are detectable in blood for weeks. Fertig and colleagues detected BNT162b2 mRNA in plasma and cellular fractions at 15 days post-vaccination (PMID 35884842). Castruita and colleagues, sequencing 108 plasma samples, found full-length or trace vaccine sequences in 10 of them, up to 28 days, and their own conclusion is that this "should lead to further research into the design of lipid-nanoparticles and the half-life of these and mRNA vaccines in humans" (PMID 36647776). Boros and colleagues documented modified mRNA and frameshifted recombinant spike products in human tissues and circulation out to months (PMID 38867495); Brogna and colleagues detected recombinant spike fragments in blood by mass spectrometry up to 187 days (PMID 37650258); and the Magen myositis case report is the sharpest single datapoint, vaccine RNA fragments mapping to only about 36 percent of the spike sequence, described by its authors as chopped, with poor antibody response and no detected spike protein (PMID 35891299).
None of that establishes intact, translation-competent mRNA at late timepoints. Gutschi's parsimonious hypothesis, that what persists is largely fragmented RNA stabilised by association with lipid remnants, including covalent lipid adducts of the kind documented in regulatory chemistry, reconciles long detection with limited evidence of late translation (her synthesis). The template question, how long germinal-centre transcription actually runs after a dose, is answered at the short end by Röltgen and colleagues (PMID 35148837). The transport question, how material keeps moving between tissues, belongs to this site's exosome-relay article. The integration question belongs to the insertional-mutagenesis defence. Keep the three separate and the honest picture fits together without anything extraordinary.
Counter-Evidence & Limitations
- The strongest LNP data are rodent and swine, mostly intravenous, at milligram-per-kilogram lipid doses. Intramuscular human dosing is a different exposure geometry. Allometric defence of high mouse doses fails, but so does allometric alarm: local concentration arguments cut both ways and neither direction is settled.
- The regulatory rat study's rising-tissue observation at 48 hours is a limit of the study, not evidence of accumulation. The Lipid 5 clearance result (complete radiolabel clearance by 168 hours) is a genuine counterweight to "the lipids never leave".
- The SM-102 versus ALC-0315 divergence in the metastasis study is one model, one endpoint, unpublished human relevance. It is a red flag for formulation-level review, not a product ranking.
- Anti-PEG findings show repertoire change at population level; the disease consequences of that change, beyond the rare anaphylaxis mechanism, are unquantified. The 2026 reviews are explicit about the gaps.
- L-DMD is a hypothesis-generating review. Its authors state the dosing-translation and human-validation limits themselves. Treating it as established mechanism would be exactly the error this site's methodology page exists to prevent.
- Epidemiological counterweights exist where they have been looked for: vaccine myocarditis risk is characterised, elevated in young males, and rare; population-level cancer signals remain contested and are not claimed here. The Wang paper is a mechanism study, not an epidemiology paper.
- The "LNPs go everywhere" slogan is as wrong as "it stays in the arm". Distribution is organ-patterned by anatomy. Overclaiming uniform distribution is the mirror error of the stay-in-the-arm claim.
What this means in practice
Not self-treatment advice; most of what follows is monitoring logic and questions for a clinician.
- Symptom geography is a distribution clue. Thyroid, eye, adrenal, renal, and small-intestinal symptoms after dosing are not random sites; they are fenestrated-capillary tissue. Report them as a pattern, with dates relative to dosing.
- Narrow-therapeutic-index drugs. If you take clozapine, warfarin, tacrolimus, phenytoin-class antiepileptics or similar, the weeks after any LNP-based product are a period for closer drug-level or effect monitoring, on the CYP evidence and the documented interaction case.
- Mitochondrial-dominant phenotype. The Mori result gives the mitochondrial-dominant subtype in the stratification article a concrete susceptibility mechanism. If that is your subtype, the case for pacing and against repeat dosing without reason strengthens.
- Reactor history. Anyone with a prior hypersensitivity reaction to an mRNA-LNP product has a plausible anti-PEG/complement mechanism on the table; that history belongs in any future consent discussion, and the pig-model authors say as much about mechanism.
- Repeat dosing multiplies every unanswered question. The interval questions (corona changes with anti-PEG titre, CYP windows overlapping, pro-metastatic windows repeating) are unmeasured for multi-dose schedules. Nobody holds the data that would answer them.
Where this sits in the site model
The particle is the third leg of the exposure story. The forensics cluster documents cargo quality (residual DNA, the SV40 enhancer, process divergence). This article documents the carrier: where it goes, what it does without any cargo, and how the immune system reads it. The persistence cluster documents the product: what spike does at the destinations. Persistent antigenic drive was always a two-factor proposition, antigen plus delivery; this page is the delivery half, and the relationships panel below wires it into the persistence, mTOR, DNA-forensics and exosome-relay pages.
The 2026 literature reads as a field beginning to do the pharmacology it skipped in 2020, whole-body PK, PBPK modelling, anti-PEG repertoire surveys, host-factor models. That work is being done by the platform's own next-generation programmes, for their own reasons. It will produce the human-adjacent data that never existed for the authorised products, and this article should be updated against it, dates and corrections in the open, per this site's correction policy.
Sources
- Seger F, Gutschi LM, Seneff S. Lipid nanoparticles as active biointerfaces: From membrane interaction to systemic dysregulation. Acta Pharm Sin B. 2026 Sep. PMID 42764981
- Grumelot, Mohammed, et al. Lipid Nanoparticle Protein Coronas Arise through Lipoprotein Fusion Rather Than Shell-like Adsorption. Nano Lett. 2026. PMID 42677364
- Mo, Liu, et al. Structural Change of ApoE–Lipid Nanoparticles Alters Receptor-Mediated Endocytosis and Induces Endosomal Disruption. J Am Chem Soc. 2026. PMID 41711348
- Francia V, Schiffelers RM, Cullis PR. The Biomolecular Corona of Lipid Nanoparticles for Gene Therapy. Bioconjug Chem. 2020. PMID 32786370
- Kimura S, Harashima H. On the mechanism of tissue-selective gene delivery by lipid nanoparticles. J Control Release. 2023. PMID 37004796
- Ci L, et al. Biodistribution of Lipid 5, mRNA, and Its Translated Protein Following Intravenous Administration of mRNA-Encapsulated Lipid Nanoparticles in Rats. Drug Metab Dispos. 2023. PMID 37208184
- Ndeupen S, et al. The mRNA-LNP platform's lipid nanoparticle component used in preclinical vaccine studies is highly inflammatory. iScience. 2021. PMID 34841223
- Mori G, et al. Mitochondrial vulnerability underlies myocarditis from COVID-19 mRNA vaccine. Nat Commun. 2026. PMID 41922346
- Yonker LM, et al. Circulating Spike Protein Detected in Post-COVID-19 mRNA Vaccine Myocarditis. Circulation. 2023. PMID 36597886
- Facskó R, et al. Anti-PEG Immunogenicity of mRNA-LNP Vaccines in Humans. Pharmaceutics. 2026. PMID 42514893
- Barta BA, et al. Comirnaty-induced cardiopulmonary distress and complement-mediated pseudo-anaphylaxis in a hyperimmune pig model. Vaccine X. 2024. PMID 38933697
- Wang, et al. Lipid nanoparticle used in mRNA vaccine promotes tumor metastasis in mouse model via mtDNA-induced neutrophil activation and NETosis. Nano Today. 2026
